A Novel No-Start Mutation in the HEY2 Gene Associated with Loss of Function and a Combined Phenotype of Arrhythmogenic Electrical Predominant Cardiomyopathy
- 1. Unit of Medical Genetics and Immunogenetics, “Madonna delle Grazie” Hospita, Italy
- 2. Clinical Pathology and Microbiology Unit, “Papa Giovanni Paolo II” Hospital, Italy
- 3. Preventive Cardiology Clinic, “Papa Giovanni Paolo II” Hospital, Italy
Abstract
Cardiomyopathies and cardiac arrhythmias represent a heterogeneous group of pathologies. If not diagnosed promptly, they can lead to serious complications such as heart failure, stroke, or sudden death. The role of medical genetics laboratories in identifying the gene mutation responsible for these heart defects is becoming increasingly significant. Identifying these diseases in the pre-clinical stage allows preventive and therapeutic strategies to be implemented which, in some cases, can save patients’ lives.
In this article, we report the case of a 64-year-old Caucasian male patient with a novel “no-start” variant NM_012259: c.-29_12del p.(?) in the Hairy Enhancer-of-split YRPW-related motif 2 (HEY2) gene, located on the long arm of chromosome 6 (6q22.31). This variant has never been described in the literature. According to the American College of Medical Genetics and Genomics (ACMG) classification, this variant is classified as probably pathogenic (class IV, PVS1, PM2).The deletion observed includes the loss of 31 nucleotides falling within the 5’ untranslated region (5’UTR) and 10 nucleotides falling within the Upstream Open Reading Frames region (nt: ATGAAGCGCC) (uORFs).
The patient with the variant found in the HEY2 gene presents hypokinetic dilated cardiomyopathy (ejection fraction 40-45%) and massive ventricular/ supraventricular arrhythmias (18,000 ventricular ectopic beats/24h), with a complex clinical picture characterized by aortic dilatation (47 mm), diffuse hypokinesia of the left ventricle and cardiac rhythm instability.
Keywords
• HEY2 gene
• Upstream Open Reading Frames region (uORFs)
• 5′ untranslated region (5’UTR region)
• Hypokinetic Dilated Cardiomyopathy
• Cardiovascular Magnetic Resonance (CMR)
• Echocardiography
Citation
Dell’Edera D, Donadio A, Rocca FL, Fausto C, Valicenti R (2026) A Novel No-Start Mutation in the HEY2 Gene Associated with Loss of Func tion and a Combined Phenotype of Arrhythmogenic Electrical-Predominant Cardiomyopathy. Ann Cardiovasc Dis 10(1): 1050.
ABBREVIATIONS
ACC: American College of Cardiology; ACM: arrhythmogenic cardiomyopathy; AHA: American Heart Association; AF: Familial Atrial Fibrillation; BrS: Brugada syndrome; CMP: Cardiomyopathies; CPVT: Catecholaminergic Polymorphic Ventricular Tachycardia; DCM: Dilated Cardiomyopathy; ESC: European Society of Cardiology; HCM: Hypertrophic Cardiomyopathy; LQTS: Long QT Syndrome; PCCD: Progressive familial Cardiac Conduction Defect; RCM: Restrictive Cardiomyopathy; SQTS: Short QT Syndrome
INTRODUCTION
Genetic cardiomyopathies are disorders of the heart muscle caused by mutations in genes that regulate the structure and function of the heart. Genetic arrhythmias are heart rhythm disorders caused by mutations in genes that alter the transmission of electrical impulses in the heart [1].
The classification of cardiomyopathies and genetic arrhythmias is fundamental for the diagnosis, treatment, and management of patients.The guidelines provided by the American College of Cardiology (ACC), the European Society of Cardiology (ESC), and the American Heart Association (AHA) provide distinct criteria, but generally agree on many of the categories [2,3].
According to the American College of Cardiology (ACC), cardiomyopathies are divided into four main categories: Dilated cardiomyopathy (DCM), Hypertrophic cardiomyopathy (HCM), Restrictive cardiomyopathy (RCM), Arrhythmogenic cardiomyopathy (ACM).
The American Heart Association (AHA) defines cardiomyopathies (CMP) as a “heterogeneous group of myocardial disorders characterized by mechanical and/ or electrical dysfunction, which generally, but not always, manifest as inappropriate ventricular hypertrophy or dilation, resulting from various causes, frequently genetic.”
The European Society of Cardiology defines cardiomyopathies as “a myocardial disorder characterized by structural and functional abnormalities of the heart muscle, in the absence of coronary artery disease, hypertension, valvular disease, and congenital heart disease sufficient to explain the observed myocardial abnormality.” As the most effective method for the diagnosis and daily management of patients, this classification system is more clinically oriented and categorizes heart muscle disorders based on ventricular morphology and function [4,5].
Based on the above, cardiomyopathies are classified as primary when the disease primarily affects the heart muscle, or as secondary when the disease is part of a broader disorder (syndromic pattern). Finally, primary cardiomyopathies can be classified as acquired, mixed (genetic and non-genetic), and hereditary.
Cardiac arrhythmias are classified by the American College of Cardiology (ACC) as: Brugada syndrome (BrS), long QT syndrome (LQTS), short QT syndrome (SQTS), familial atrial fibrillation (AF), catecholaminergic polymorphic ventricular tachycardia (CPVT), and progressive familial cardiac conduction defect (PCCD).
Hereditary cardiac arrhythmias are rare conditions and often cause sudden death in young adults. They result from a series of mutations affecting various genes that control the function of ion channels and the proteins involved in their regulation. Since the alterations affect ion channels, they are also known as channelopathies [6-8].
A better understanding of genetics is important for identifying patients in the preclinical stage, who are unaware that they have a genetic defect that will cause them to develop cardiomyopathy or arrhythmia.
This article reports on a study conducted on a 64-year-old man with hypokinetic dilated cardiomyopathy (EF 40-45%), massive ventricular/supraventricular arrhythmias (18,000 ventricular ectopic beats - VEB/24h), aortic dilatation (47 mm), diffuse hypokinesia of the left ventricle, and cardiac rhythm instability.
The genetic study found for the first time the presence of the “no-start” variant NM_012259: c.-29_12del p.(?) in a heterozygous state in the Hairy Enhancer-of-split related with YRPW motif 2 (HEY2) gene located on the long arm of chromosome 6 (6q22.31) (dbSNP: rs759494126). According to the classification of the American College of Medical Genetics and Genomics (ACMG), this variant is classified as probably pathogenic (class IV, PVS1, PM2). In silico predictor values are: CADD 23.6, SpliceAI 0.00, Pangolin 0.0200, phyloP 3.97.
The HEY2 protein acts as a transcriptional repressor and helps maintain ventricular electrophysiological identity, cell junction organization, and myocardial homeostasis. Therefore, its reduction can produce a cardiac phenotype that initially leads to electrophysiological rather than structural alterations.
MATERIALS AND METHODS
Patient Information, History of Present Illness and Physical Examination:
The subject is a 64-year-old man of Italian origin, normotensive (BP: 120/70 bpm), euglycemic, euthyroid, with mild dyslipidemia and no gastroesophageal reflux disease (GERD).
The Holter dynamic electrocardiogram detected: a heart rate between 120 and 33 beats per minute (bpm), approximately 760 non-periodic premature ventricular contractions (PVCs), and approximately 9.000 ventricular extrasystoles occurring episodically in pairs. Cardiovascular Magnetic Resonance (CMR) was performed using Siemens Magnetom Aerea 1.5 Tesla equipment, using Gadovist as the contrast agent (CA), administered intravenously at a dose of 0.15 mmol/kg [9].
Sequences were used to assess cardiac function (cine-SSFP), edema (TIRM, T2, and T2 mapping), fibrosis (T1 and T2 mapping), perfusion, and myocardial necrosis (PSIR and LGE) after administering the contrast agent.
CMR revealed dilation of the aortic root (maximum diameter of approximately 47 mm) and ascending aorta (maximum diameter of approximately 41 mm), while the atria and heart valves were normal.
Diffuse segmental hypokenesia was observed with moderate reduction in global systolic function (EF=40%); no clear signal alterations suggestive of myocardial edema were detected in the TIRM T2 sequences; no alterations in myocardial relaxation times were observed in the T1 and T2 mapping sequences; no areas of scarring (fibrosis) or myocardial necrosis were observed in the PSIR and LGE sequences after contrast medium administration.
Clinical Findings and Investigations.
These investigations led to the clinical conclusion that the subject had dilated cardiomyopathy, in the absence of clear alterations in tissue characterization. A genetic study was conducted to better understand the phenotype-genotype association.
The molecular test we use is based on the principle of massive parallel sequencing (Next Generation Sequencing, NGS). This has made it possible, using a commercial kit (SOPHiA EXTENDED CARDIO SOLUTION™ Kit), to
simultaneously study 128 genes involved in the hereditary transmission of certain cardiomyopathies and cardiac arrhythmias (the tested gene list is shown in Table 1).
Table 1: The tested gene list.
ABCC9, ACTA1, ACTC1, ACTN2, AKAP9, ALPK3, ANK2, ANKRD1, APOA1, ATP2A2, BAG3, CACNA2D1, CACNAIC, CACNB2, CALM1, CALM2, CALM3, CALR3, CASQ2, CAV3, CHRM2, CRAYB, CSRP3, CTF1, CTNNA3, DES, DMD, DOLK, DPP6, DSC2, DSG2, DSP, DTNA, EMD, EYA4, FGF12, FHL1, FHL2, FKTN, FLNC, GAA, GATA4, GATA6, GATADI, GJA1, GJA5, GJC1, GLA, GPD1L, HCN4, HEY2, HFE, JPH2, JUP, KCNA5, KCNAB2, KCND3, KCNE1, KCNE2, KCNE3, KCNE5, KCNH2, KCNJ2, KCNJ5, KCNJ8, KCNQ1, LAMA4, LAMP2, LDB3, LMNA, MYBPC3, MYH6, MYH7, MYL2, MYL3, MYLK2, MYOM1, MYOZ2, MYPN, NEBL, NEXN, NKX2-5, NOS1AP, NPPA, NUP155, PDLIM3, PKP2, PLN, PRDM16, PRKAG2, PSEN1, PSEN2, PTPN11, RAF1, RANGRF, RBM20, RYR2, SCN10A, SCN1B, SCN2B, SCN3B, SCN4B, SCN5A, SCO2, SGCD, SLC8A1, SLMAP, SNTA1, STRN, SURF1, TAZ, TBX20, TBX5, TCAP, TGFB3, TMEM43, TMPO, TNNC1, TNNI3, TNNT2, TPM1, TRDN, TRPM4, TRPM7, TTN, TTR, VCL.
GENETIC TESTING
Sample Collection and Genomic DNA Extraction
Venous blood samples were collected in tubes containing ethylenediaminetetraacetic acid-K3 (EDTA-K3) as an anticoagulant. Genomic DNA was isolated from leukocytes using the MagCore automated extractor (RBC Bioscience, Taiwan). The automated protocol ensures consistent yields and high purity, minimizing operator variability. Extractions were performed according to the manufacturer’s instructions, and purified genomic DNA was stored at −20°C until use. DNA purity and concentration were assessed by spectrophotometry using the Implen NanoPhotometer N60 (Implen GmbH, Germany), recording the absorbance ratios of 260/280 and 260/230 to check for protein contaminants. Quantitative DNA assay was performed using the Qubit 4.0 fluorimeter (ThermoFisher Scientific Holdings Europe Ltd, UK) with the Qubit dsDNA High Sensitivity kit, which allows for accurate measurement of double-stranded DNA content.
Library Preparation and Target Enrichment
Target enrichment was performed using the Sophia Genetics Extended Cardio Solution (ExtCas) panel. This panel includes the simultaneous study of 128 genes related to the manifestation of genetically based cardiomyopathies and/or arrhythmias (Sophia Genetics, 401 Park Drive, 5TH Floor, Boston, MA 02215, USA). Library preparation was conducted according to the manufacturer’s instructions, with minor operational modifications introduced to improve uniformity of coverage. Polymerase Chain Reaction (PCR) steps were performed on a VeritiPro Thermal Cycler (ThermoFisher Scientific Holdings Europe Ltd, UK).
After amplification, PCR products were purified by magnetic separation to remove adapter dimers and small fragments. Library concentration was verified by fluorimetry, and fragment size distribution was analyzed using the Agilent 4200 TapeStation System (Agilent Technologies, 5301 Stevens Creek Blvd., Santa Clara, CA 95051, USA) to confirm the expected amplification profile before sequencing.
Sequencing and Bioinformatics Analysis
Normalized libraries were pooled in equimolar quantities and sequenced on the Illumina MiSeq Dx platform (Illumina Inc., USA), using the MiSeq Reagent Kit V2 in a 250-bp paired-end configuration. This setup ensured an optimal balance between sequencing depth and accuracy, allowing for the reliable identification of single nucleotide variants (SNVs) and small insertions or deletions. Each sequencing run included negative extraction controls and positive reference samples to monitor for contamination and evaluate overall run performance. FASTQ files were automatically generated using MiSeq Reporter software.
Primary data processing, including demultiplexing, adapter trimming, and alignment to the GRCh37 (hg19) human reference genome, was performed using Sophia DDM software V7 (Sophia Genetics, Switzerland). Variant calling and annotation were performed using Sophia Genetics’ proprietary algorithms, integrating curated databases such as ClinVar, COSMIC, and dbSNP. Quality control parameters (mean depth of coverage, uniformity, and percentage of on-target reads) were analyzed for each sample to ensure data reliability and reproducibility.
DISCUSSION
Molecular testing identified the presence of the heterozygous variant c.-29_12del p.(?) in the Hairy Enhancer-of-split related with YRPW motif 2 (HEY2, NM_012259) gene. The Sophia DDM software V7 (Sophia Genetics, Switzerland), using the criteria of the American College of Medical Genetics and Genomics (ACMG), classifies this variant as “probably pathogenic” (class IV, PVS1, PM2) (Figure 1).
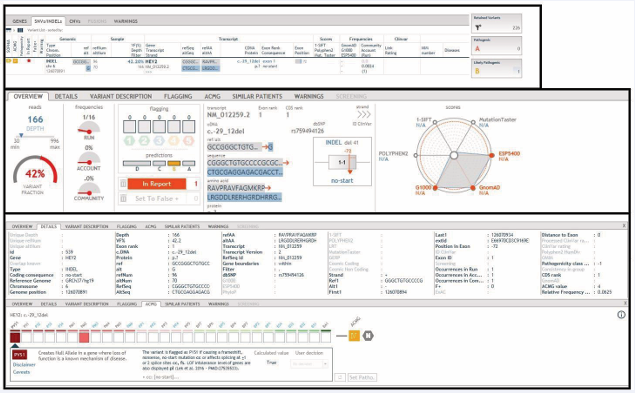
Figure 1: HEY2 gene (NM_012259), variant c.-29_12del p.(?) in heterozygous. The “Sophia DDM software”, using the criteria of the American College of Medical Genetics and Genomics (A.C.M.G.), classifies this variant as “probably pathogenic” (class IV, PVS1, PM2).
The deletion observed includes the loss of 31 nucleotides falling within the 5′ untranslated region (5’UTR) and 10 nucleotides falling within the Upstream Open Reading Frames (uORF) region (nt: ATGAAGCGCC) (Figure 2) [10].

Figure 2: The deletion involves the loss of 31 nucleotides in the 5’UTR region and 10 nucleotides in the upstream open reading frame (NT: ATGAAGCGCC). The deletion removes a regulatory sequence that consequently leads to increased expression of the HEY2 protein (IGV software).
This gene encodes a member of the basic helix-loop-helix (bHLH) transcription factor family, hairy and enhancer of split-related (HESR). The encoded protein is localized in the nucleus and interacts with a histone deacetylase complex to repress transcription. The expression of this gene is induced by the Notch signal transduction pathway [11].
Data in the literature show that redution Hey2 expression in adult patients with cardiomyopathy (CM) causes contractile dysfunction and mortality [12], as well as in patients with dilated cardiomyopathy (DCM). Increased HEY2 expression has also been reported in patients with heart failure [13]. RNA-seq confirmed that there is a reduced expression of the mutated allele resulting from the heterozygous deletion in the HEY2 gene (RNAwt: 80%, RNAdel: 20%).
The most striking finding in this case study is not the 40% EF, but approximately 760 nonperiodic ventricular extrasystoles (PVCs) and approximately 9,000 ventricular extrasystoles that occurred episodically in pairs. This suggests widespread electrical instability. Experimental models of reduced HEY2 function have observed altered expression of sodium channels, potassium channels, and proteins involved in impulse propagation. In the long run this leads to the development of PVC- induced cardiomyopathy (chronic extrasystole, functional remodeling, reduction of ejection fraction).
When observed it is partly confirmed by a positive family history: the proband (family tree III2) shows that the paternal grandmother (family tree I2) had an cardioverter defibrillator fitted (ICD) (documentation not available as she died at the age of seventy-five); the father of the proband (family tree II1) died of suspected sudden cardiac death at the age of sixty-seven (SCD); the two sisters of the proband (family tree III1 and III3) underwent cardiological examinations and genetic testing, which found no cardiac abnormalities or the presence of the c.-29_12del p.(?) variant in the HEY2 gene (Figure 3).
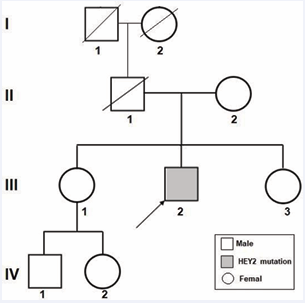
Figure 3: Pedigree. Proband (II2) identified by the arrow. Square: male; circle: female; shaded: affected by cardiomyopathy and with a mutation in the HEY2 gene
CONCLUSION
In this study, we report for the first time the heterozygous variant NM_012259:c.-29_12del p.(?) in the Hairy Enhancer-of-split related with YRPW motif 2 (HEY2) gene located on the long arm of chromosome 6 (6q22.31) and its association with “arrhythmogenic electrical-predominant cardiomyopathy associated with partial loss of HEY2 function”. The deletion eliminates the start codon and reduces gene activity; reduced HEY2 activity alters ventricular electrophysiological regulation; compare this with a high rate of ventricular extrasystoles; chronic arrhythmia induces moderate systolic dysfunction without evident fibrosis; the alteration of the Notch/HEY2 pathway itself may contribute to the observed aortic dilation. Table 2 provides a summary of the evidence provided by the ACMG.
Table 2: Summary of ACMG evidence
|
Parameter |
Detail |
|
HEY2 gene |
Hairy/Enhancer-of-split related with YRPW motif 2 |
|
Genomic location |
Chromosome 6q22.31 |
|
Variant type |
No-start deletion: NM_012259: c.-29_12del p.(?) |
|
Affected region |
5’UTR (−31 nt) + uORF (−10 nt) |
|
Molecular effect |
Loss of start codon → absence of translation → loss-of-function |
|
ACMG classification |
Class IV – Likely Pathogenic (PVS1 + PM2 + PP3 + PP4) |
|
Population frequency |
Absent from gnomAD, ClinVar, HGMD |
|
Biological role |
Cardiac development, ventricular differentiation, electrical conduction |
|
Structural phenotype |
Hypokinetic DCM (EF 40–45%), diffuse LV hypokinesia |
|
Electrical phenotype |
18,000 PVCs/24h, complex ventricular and supraventricular arrhythmias |
|
Aortic findings |
Aortic dilation 47 mm |
|
Genotype–phenotype correlation |
Consistent with HEY2 loss-of-function: cardiomyopathy, arrhythmias, aortic abnormalities |
|
Literature evidence |
HEY2 linked to structural defects, arrhythmias, CHD, aortic anomalies |
|
Clinical implications |
Arrhythmic risk, DCM progression, family screening, tailored follow-up |
The results reported here suggest a likely pathogenic effect of this variant and could serve as a springboard for functional studies aimed at better understanding the molecular pathways involved.
Ethics Approval and Consent to Participate
This study complies with the ethical standards of the institutional and/or national research committee and with the 1964 Declaration of Helsinki and its later amendments. Written informed consent was obtained from the patient for participation.
Consent For Publication
Written informed consent was obtained from the patient and the patient’s parent to write and publish this case report. A copy of the written consent is available for review by the Editor-inChief of this journal.
ACKNOWLEDGMENTS
We thank the Volunteer Organizations (ODV) Gian Franco Lupo and Anima Mundi. The authors would like to thank their families for their help and participation in the study.
REFERENCES
- Hayesmoore JB, Bhuiyan ZA, Coviello DA, du Sart D, Edwards M, Iascone M, et al. EMQN: Recommendations for genetic testing in inherited cardiomyopathies and arrhythmias. Eur J Hum Genet. 2023; 31: 1003-1009.
- L. Maximilian Buja, Jagdish Butany. Cardiovascular Pathology. 5th Edition. 2022.
- Hershberger RE, Givertz MM, Ho CY, Judge DP, Kantor PF, McBride KL, et al. Genetic Evaluation of Cardiomyopathy-A Heart Failure Society of America Practice Guideline. J Card Fail. 2018; 24: 281-302.
- Chou C, Chin MT. Genetic and Molecular Mechanisms of Hypertrophic Cardiomyopathy. Int J Mol Sci. 2023; 24: 2522.
- Elliott P, Schunkert H, Bondue A, Behr E, Carrier L, Van Duijn C, et al. Integration of genetic testing into diagnostic pathways for cardiomyopathies: a clinical consensus statement by the ESC Council on Cardiovascular Genomics. Eur Heart J. 2025; 46: 344-353.
- Corrado D, Anastasakis A, Basso C, Bauce B, Blomström-Lundqvist C, Bucciarelli-Ducci C, et al. Proposed diagnostic criteria for arrhythmogenic cardiomyopathy: European Task Force consensus report. Int J Cardiol. 2024; 395: 131447.
- Fu DG. Cardiac Arrhythmias: Diagnosis, Symptoms, and Treatments. Cell Biochem Biophys. 2015; 73: 291-296.
- Hauer RN, Aliot E, Block M, Capucci A, Lüderitz B, Santini M, et al. Indications for implantable cardioverter defibrillator (ICD) therapy. Study Group on Guidelines on ICDs of the Working Group on Arrhythmias and the Working Group on Cardiac Pacing of the European Society of Cardiology. Eur Heart J. 2001; 22: 1074-1081.
- Pugliese L, Luciano A, Chiocchi M. The Role of Cardiac Magnetic Resonance Imaging in the Management of Hypertrophic Cardiomyopathy. J Cardiovasc Dev Dis. 2025; 12: 189.
- Robinson JT, Thorvaldsdottir H, Turner D, Mesirov JP. igv.js: an embeddable JavaScript implementation of the Integrative Genomics Viewer (IGV). Bioinformatics. 2023; 39: btac830.
- She P, Gao B, Li D, Wu C, Zhu X, He Y, et al. The transcriptional repressor HEY2 regulates mitochondrial oxidative respiration to maintain cardiac homeostasis. Nat Commun. 2025; 16: 232.
- van Walree ES, Dombrowsky G, Jansen IE, Mirkov MU, Zwart R, Ilgun A, et al. Germline variants in HEY2 functional domains lead to congenital heart defects and thoracic aortic aneurysms. Genet Med. 2021; 23: 103-110.
- Das S, Frisk C, Eriksson MJ, Walentinsson A, Corbascio M, Hage C, et al. Transcriptomics of cardiac biopsies reveals differences in patients with or without diagnostic parameters for heart failure with preserved ejection fraction. Sci Rep. 2019; 9: 3179.